

Short answer
An adrenaline dump isn’t a formal diagnosis. It’s patient language for a sudden sympathetic surge: your heart pounds, your hands shake, your stomach flips, you may feel chilled or flushed, and your body feels wired even if you are not scared. In POTS, this can happen because your circulation is already working hard to keep blood moving back to your heart and brain. When blood pools, blood volume is low, or the autonomic nervous system misreads the threat level, the body may compensate with a bigger-than-needed “fight-or-flight” push. POTS sources describe this same physiology as excessive heart-rate rise, increased norepinephrine while upright, altered brain blood flow, palpitations, tremulousness, nausea, fatigue, and brain fog. (dysautonomiainternational.org)
The surge itself is usually short — minutes to about an hour. There is no formal POTS duration criterion for it, so the nearest documented comparator is the panic attack, which NIMH describes as lasting "from a few minutes to an hour or sometimes longer." (nimh.nih.gov) Formal POTS guidance does not give one fixed duration for an “adrenaline dump,” because the term is not a clinical endpoint; clinicians usually track posture, heart rate, blood pressure, symptoms, triggers, and recovery instead. The part many people underestimate is the tail: after the obvious rush fades, your nervous system may still feel spent. The next day can feel flat, foggy, heavy, and strangely “hungover,” especially when you stand up again.
A surge does not reset overnight — and we can show you the tail
We looked at what happens on the days after a sympathetic surge — the part almost nobody measures — across 4,145 Welltory users and 367,569 tracked days (wearable-quality data only).
We defined a surge day the way people describe a dump: a day when resting heart rate sat at least 1 standard deviation above that person's own baseline, with no matching rise in activity. A racing body on a day the body wasn't working harder. Those days are not rare — 8.7% of all tracked days, roughly one day in eleven.
Here is what the days that followed looked like, against the days after a calm day (resting heart rate within ±0.5 SD of that person's own baseline, same activity condition):
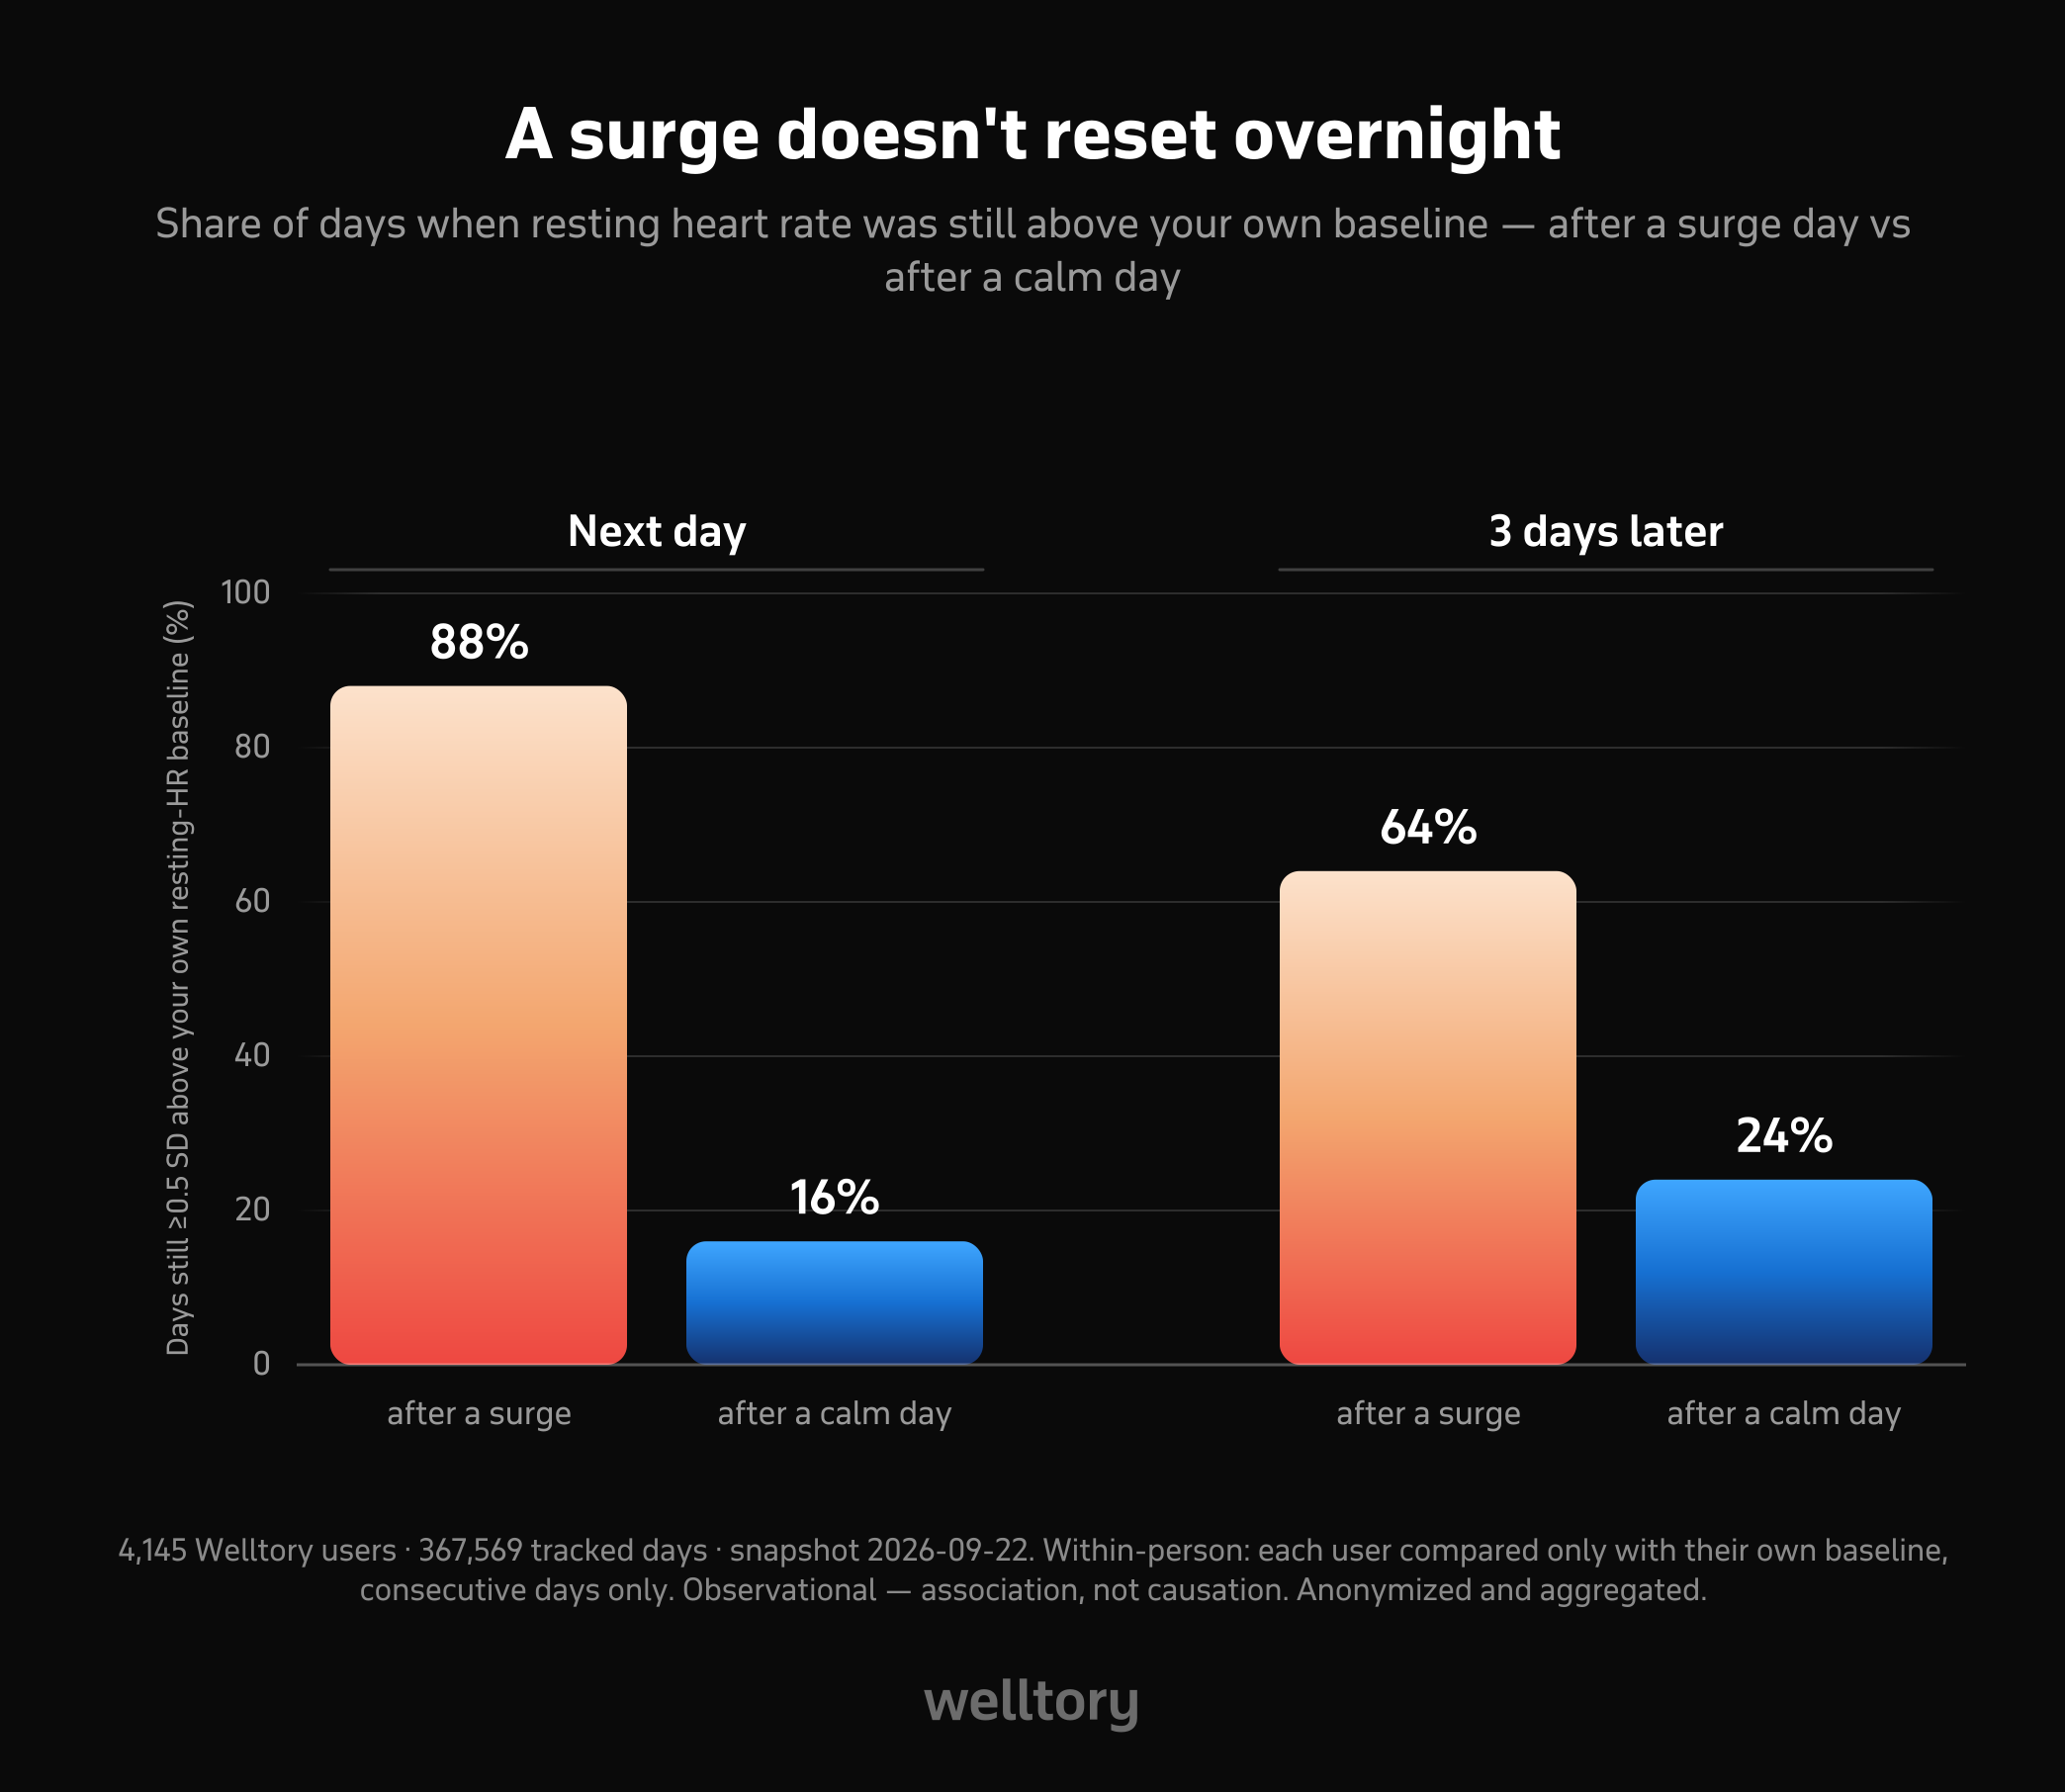
A surge is not a spike that clears by morning. In this data it opens a multi-day elevated stretch: on 88% of next days the body was still running above its own normal, and on roughly two out of three third days it still had not come all the way back. That is a number for the thing patients keep being told is imaginary — the "adrenaline hangover."
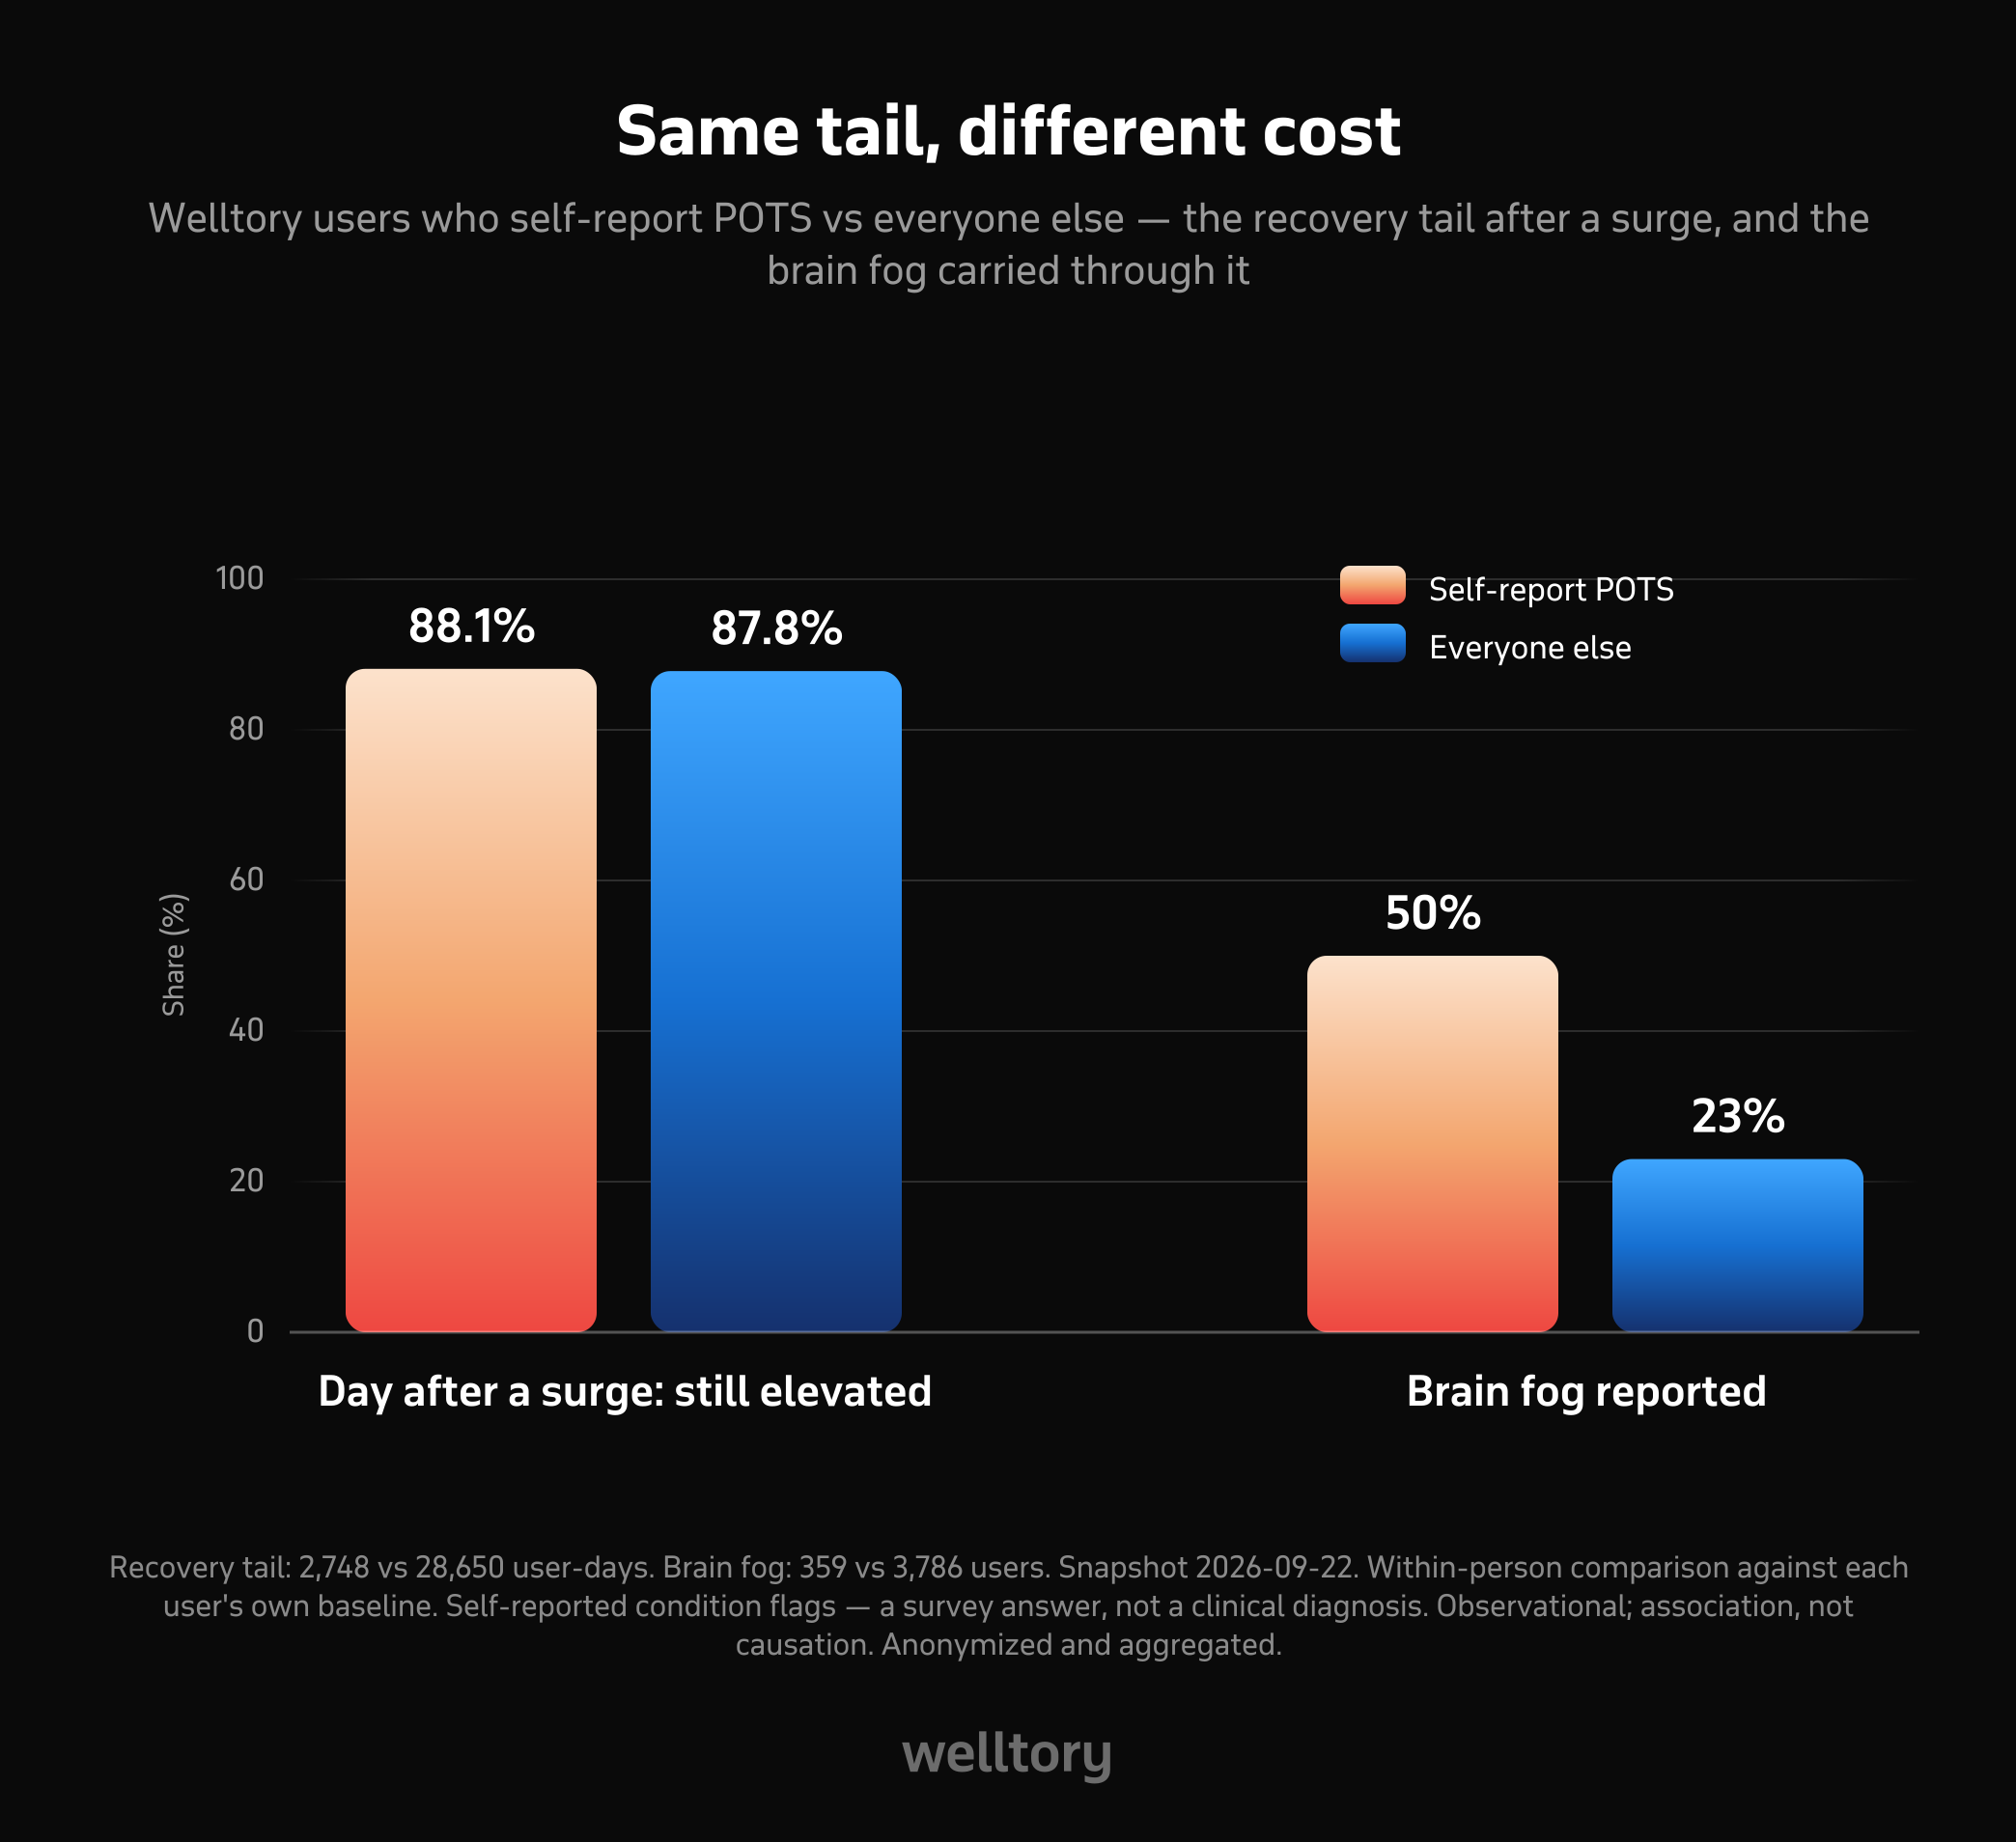
Two honest points about who this applies to. First, the tail was the same for Welltory users who self-report POTS and for everyone else — 88.1% vs 87.8% on the next day, 75.5% vs 74.2% on day two. The multi-day tail after a surge is not POTS-specific; it looks like how autonomic arousal behaves in general. Second, what is markedly different in the self-report POTS group is the symptom load carried through that tail: brain fog was reported by 50% of 359 users who self-report POTS versus 23% of 3,786 comparison users, and that gap holds up when we compare people with the same number of other conditions — so it tracks with POTS itself.
Which gives the most useful framing we can offer: the surge tail is ordinary physiology. Living through a three-day tail with POTS costs far more than living through it without.
Association, not causation. These are observational data from people who chose to track, and the POTS group is self-identified in a survey, not clinically diagnosed.
Adrenaline dump at a glance
An adrenaline dump is the name many people with POTS use for a sudden autonomic surge: your heart starts pounding or racing, your body may shake, sweat, flush, chill, feel nauseated, or feel urgently “activated,” even when you are not scared. In POTS, this can happen because the autonomic nervous system is struggling to keep blood flow stable when you sit up or stand; in the hyperadrenergic pattern, sympathetic “fight-or-flight” symptoms like palpitations, tachycardia, anxiety-like activation, and tremor can be especially prominent. (my.clevelandclinic.org)
The trigger is not always obvious. A dump can follow standing, standing too long, heat, a large or carbohydrate-heavy meal, dehydration, illness, menstruation, alcohol, or a rough night of sleep. It can also feel like it came out of nowhere, because the body’s compensation may be happening before your conscious mind has a story for it. (potsuk.org)
The onset is usually fast: POTS symptoms can appear immediately or within a few minutes after sitting up or standing. That is why the surge often feels like a switch flipped, not like a slow emotional build. (my.clevelandclinic.org)
The intense part is usually short — more like minutes than an all-day state. “Up to about an hour” comes from panic-like autonomic episodes — NIMH puts a panic attack at a few minutes to an hour or sometimes longer (nimh.nih.gov) — and it is not a formal POTS duration criterion. Clinically, palpitations often last seconds or minutes and can sometimes last longer; panic attacks are commonly described as lasting 5–20 minutes, with some reported up to an hour. (my.clevelandclinic.org)
What makes a POTS dump different from “just anxiety” is the body-first pattern. You may notice the racing heart, tremor, nausea, flushing, chills, chest tightness, or urge to move before any specific fear shows up. POTS is also commonly confused with panic disorder or chronic anxiety because the symptoms overlap, but orthostatic intolerance has a circulatory and autonomic driver, not simply a thought-based trigger. (pmc.ncbi.nlm.nih.gov)
Afterward, you may not snap back to baseline. The surge can leave you wiped out, foggy, shaky, headachy, or “crashed” for the rest of the day, especially if it followed poor sleep, heat, illness, prolonged standing, or a meal. Fatigue and brain fog are common POTS symptoms, and cognitive symptoms can persist even after lying down in some patients. (my.clevelandclinic.org)
What an adrenaline dump actually is
An “adrenaline dump” is not a formal POTS diagnosis. It’s the name people use for a very real body state: your autonomic nervous system suddenly pushes you into a fight-or-flight pattern — fast pulse, shaky limbs, tight chest, sweating, a wired feeling — even when nothing dangerous is happening around you.
Your autonomic nervous system runs heart rate and blood vessel tone without asking you. "The SNS mediates the "fight or flight" response via catecholamines, increasing heart rate, contractility, and vasoconstriction, whereas the PNS promotes restorative processes through acetylcholine, decreasing heart rate and enhancing vasodilation." In plain English: one branch speeds you up and tightens vessels so blood can move under pressure; the other helps you slow down, digest, recover, and return to baseline. (ncbi.nlm.nih.gov)
Catecholamines are the chemical family behind the surge. "body systems outside the brain that use the catecholamines dopamine (DA), norepinephrine (NE), and epinephrine (EPI) as chemical messengers" Epinephrine and norepinephrine can raise heart rate, increase cardiac output, tighten blood vessels, and create the familiar “charged” feeling of fight-or-flight. (ncbi.nlm.nih.gov)
In POTS, the sequence usually runs backwards from what people expect. The body is often not starting with fear. It is starting with circulation. When you stand, gravity pulls more blood into the lower body. In many people with POTS, blood vessels do not tighten efficiently enough, so too much blood stays below the heart, less returns upward, and the brain reads that as a supply problem. The sympathetic system then compensates — harder and faster than needed — by releasing epinephrine and norepinephrine and driving the heart rate higher. Tachycardia here is a signal of orthostatic stress, not the whole disease itself. (hopkinsmedicine.org) This blood-pooling route is one of several recognised mechanisms: reviews of POTS describe "mechanistic phenotyping within POTS (low-preload/pooling dominant, neuropathic, hyperadrenergic, immune-associated, and secondary structural/CSF-pressure contributors)" — so the low-preload/pooling pattern above describes one phenotype, not every case.
That is why the surge can feel so confusing. You may be standing in line, sitting after a trigger, or trying to sleep when your body flips into alarm mode. POTS can include racing or forceful heartbeats, shakiness, sweating, chest discomfort, disrupted sleep, and symptoms that worsen with upright posture, heat, illness, dehydration, or exertion. The body is not necessarily reacting to danger. It may be over-correcting for unstable blood flow — and the correction can feel exactly like panic from the inside. (hopkinsmedicine.org)
What an adrenaline dump feels like
An “adrenaline dump” isn’t a formal diagnosis. It’s the phrase many people with POTS use for a sudden sympathetic surge: your heart speeds up, your body acts as if something urgent is happening, and the sensation can feel wildly out of proportion to the moment. That fits with the broader POTS symptom pattern clinicians describe — palpitations or racing heart rate, shakiness, sweating, nausea, fatigue, feeling nervous or anxious, and symptoms that can flare with standing, heat, illness, exertion, or hormonal shifts. Dysautonomia can also affect sweating, skin temperature, digestion, bladder signals, and sleep, which is why the episode can feel like a whole-body event rather than “just” a fast pulse. (my.clevelandclinic.org)
The cluster people describe most consistently:
heart pounding or racing, sometimes with a skipped-beat sensation
shaking or inner tremor, often in the hands and legs
nausea, occasionally vomiting
chills, goosebumps, or a hot flush — sometimes both in sequence
cold, clammy hands and feet
a sense of dread or urgency without a thought attached to it
needing to urinate shortly afterwards
feeling wired, unable to settle, then abruptly drained
The detail that matters diagnostically: the physical symptoms arrive first and the emotional interpretation arrives second. People often say they feel their body panic before they feel afraid. That distinction matters because POTS can be mistaken for anxiety or panic, partly because many symptom checklists for anxiety include the same body sensations — palpitations, trembling, breathlessness, nausea, sweating. But research on POTS and panic-like symptoms suggests the overlap is largely somatic: the body alarm is real, and the fear may come from trying to interpret what the body is doing. (ahajournals.org)
Adrenaline dump vs panic attack: how to tell them apart
This distinction gets missed because the body language overlaps: racing heart, shaking, nausea, chest tightness, dizziness, dread. A panic attack can feel intensely physical, not “imaginary.” But POTS can also look like panic when your autonomic nervous system is trying to keep blood moving to your brain while you’re upright. Dysautonomia International notes that POTS is often mistaken for anxiety or panic disorder, while NIMH describes panic attacks as sudden waves of fear or discomfort with symptoms such as racing heart, trembling, dizziness, nausea, chest pain, and fear of losing control or dying. The clue is not whether it feels scary. The clue is what starts it, what keeps it going, and what helps it stop. (dysautonomiainternational.org)
| | Adrenaline dump (dysautonomic surge) | Panic attack |
|---|---|---|
| Starts with | Body symptoms first — heart racing, tremor, nausea, heat, weakness, “wired” feeling | Often fear, alarm, a thought, a place, or a sense of danger first |
| Fear content | Diffuse dread: “something is wrong with my body,” often without a clear story | More often a specific fear: dying, losing control, fainting in public, being trapped |
| Position | Often linked to standing, heat, dehydration, a shower, exertion, or eating | Not typically postural; can happen at rest or during sleep |
| Heart rate pattern | Rises with upright posture and may stay high until you sit or lie down | Rises with the fear wave and usually settles as the panic settles |
| Response to reassurance | Reassurance may help your mind, but the physiology can keep running | Often eases as the fear loop eases, especially with grounding, breathing, or support |
| After | Flat, foggy, shaky, sometimes a crash that lasts into the next day | Drained or embarrassed, but the “after” is often shorter |
Both are real. They can also coexist: you can have POTS and panic attacks, and one diagnosis does not erase the other. The reason to separate them is practical. If the surge is driven by orthostatic blood pooling and low effective circulating volume, the plan usually leans toward fluids, salt if appropriate for you, compression, trigger management, and pacing; POTS consensus guidance and Dysautonomia International both describe volume expansion, compression, and exercise-based reconditioning as common management tools. If the main driver is panic disorder, treatment usually points in a different direction, such as psychotherapy and, for some people, medication. (pmc.ncbi.nlm.nih.gov)
So the question is not “Is this anxiety or is this physical?” Panic is physical. POTS is physical. The better question is: does your body surge because your brain detected danger, or does your brain detect danger because your body is surging? Being told “it’s just anxiety” when the mechanism is circulatory is a common wrong turn in POTS care — and it can delay the basic supports your body was asking for. (dysautonomiainternational.org)
How long does an adrenaline dump last — and what about the 24 hours after?
The surge is short. The recovery is not.
For the acute “adrenaline dump” itself, formal POTS criteria do not define a standard episode length. Patient descriptions put the peak at minutes to roughly an hour, in the same range NIMH gives for a panic attack (nimh.nih.gov). What is better documented is the pattern around it: POTS symptoms often appear or worsen with being upright, and they can include racing heart, palpitations, shakiness, sweating, chest discomfort, fatigue, and brain fog. In hyperadrenergic POTS, the same upright stress can come with stronger sympathetic activation — tremor, anxiety-like body sensations, tachycardia, and higher standing norepinephrine. (hopkinsmedicine.org)
What follows the surge may be the part that actually steals your day. PoTS UK describes tiredness or weakness as common and able to last “a considerable time” after a flare, and also describes brain fog as trouble thinking, focusing, finding words, or communicating — often worsened by dehydration, poor sleep, prolonged standing, heat, pain, fatigue, or feeling faint. Dysautonomia International’s orthostatic intolerance summary also notes that fatigue after exertion or sustained upright activity can last 24–72 hours in some patients. That does not prove every adrenaline dump has a 24-hour tail, but it does make the “next-day crash” many people describe physiologically believable. (potsuk.org)
Mechanistically, this is not “just stress.” In POTS, standing can mean less stable blood return and less steady blood flow to the brain; the nervous system may keep releasing epinephrine and norepinephrine to tighten blood vessels and push heart rate up. That compensation can feel like fear even when you are not emotionally afraid: pounding heart, shaky limbs, heat, chest tightness, urgency, and a body that will not settle on command. (hopkinsmedicine.org)
The “adrenaline hangover” explanation is best treated as a practical model, not a proven POTS mechanism — and the pharmacology argues against the literal version of it. Circulating epinephrine is cleared fast: its plasma half-life is under five minutes (ncbi.nlm.nih.gov), so a next-day crash cannot be the hormone still sitting in your blood. Strong or prolonged catecholamine signaling can make beta-adrenergic receptors less responsive or downregulated in experimental and physiologic studies, but that does not mean a POTS crash is simply “adrenaline depletion.” A safer way to think about it: your body has just spent a lot of autonomic effort trying to keep you upright and perfused. Afterward, the same nervous system may be easier to provoke, while your brain and muscles have less margin. (pubmed.ncbi.nlm.nih.gov)
This is where our own data is blunt. After a heart-rate surge that activity does not explain, resting heart rate was still above the person's own baseline on 88% of next days and 64% of third days — against 16% and 24% after a calm day (4,145 users, 367,569 tracked days; full numbers and controls in How we made it). The tail is real, it is measurable in your own baseline, and it lasts days rather than hours.
Practical consequence: do not plan the day after a surge as if nothing happened. The 24-hour window is the part worth protecting. More fluids and salt if your clinician has recommended them, compression, cooler environments, smaller tasks, fewer long standing blocks, and permission to lie down early are not “being dramatic.” They are ways to reduce the odds that yesterday’s dump becomes today’s flare. POTS symptoms are known to worsen with heat, prolonged standing, strenuous activity, illness, inadequate fluid or salt intake, and sometimes after missed meals — exactly the conditions people often push through when they are trying to “catch up.” (my.clevelandclinic.org)
What sets off a dump
A dump usually starts when your circulation is already under load and your body has to compensate harder. The classic setup is upright posture: getting up quickly, standing still too long, or sitting upright without moving much. Blood has more time to pool in the abdomen and legs, less returns to the heart, and the autonomic nervous system pushes harder to keep blood moving to your brain — which can feel like a sudden surge rather than a slow “POTS flare.” Heat makes the same problem louder: a hot shower, hot room, summer weather, or an overheated commute can widen blood vessels and worsen pooling, so your heart rate may jump faster. (potsuk.org)
Food can do it too, especially a large meal or a meal heavy in refined carbohydrates. Digestion pulls more blood toward the gut; in POTS, that extra demand can leave you feeling more tachycardic, shaky, foggy, or wiped out after eating. PoTS UK specifically notes that some people feel worse after high-carbohydrate meals because blood is diverted to the gut for digestion, and a POTS study found high-carbohydrate intake can worsen upright tachycardia in susceptible patients. Dehydration, missed fluids, and not getting enough salt for your own care plan can lower the buffer even more. (potsuk.org)
Sleep debt is another quiet trigger. If the night before was fragmented, too short, or unrefreshing, you may start the day with less autonomic “room” to adapt. PoTS UK lists poor sleep, dehydration, prolonged standing, excessive heat, and pain as common brain-fog triggers, and Dysautonomia International notes that many people with POTS need more sleep and flexible scheduling because symptoms can flare without much warning. (potsuk.org)
Hormones can change the threshold too. Some people notice worse symptoms before or during a period; research in people with POTS found lightheadedness varied across the menstrual cycle and peaked during menses, while PoTS UK lists menstrual periods among factors that can worsen symptoms. Infection is another common amplifier: symptoms may worsen while you are ill, and recovery may take longer than expected. (pubmed.ncbi.nlm.nih.gov)
And “exertion” does not only mean a workout. A long conversation, a stressful meeting, problem-solving for hours, sensory overload, conflict, excitement, or any sudden emotional load can push the same system. Physical exertion can exacerbate POTS symptoms, and PoTS UK notes that people with PoTS can be sensitive to physical and psychological stressors. If you also have ME/CFS, the overlap matters: CDC describes post-exertional malaise as symptom worsening after even minor physical or mental exertion, often delayed by 12–48 hours and lasting days or weeks. In that case, the POTS surge and the ME/CFS crash can stack — first the adrenaline-like spike, then the delayed payback. (potsuk.org)
Hyperadrenergic POTS: when dumps are the pattern, not the exception
POTS is not one thing. Current framing separates mechanistic subtypes — pooling-dominant, neuropathic, hyperadrenergic, immune-associated. "mechanistic phenotyping within POTS (low-preload/pooling dominant, neuropathic, hyperadrenergic, immune-associated, and secondary structural/CSF-pressure contributors)" Older consensus language says the same idea in a broader way: POTS can involve different mechanisms, including autonomic denervation, low blood volume, hyperadrenergic stimulation, deconditioning, and heightened body-signal monitoring — and those mechanisms can overlap in one person. (pmc.ncbi.nlm.nih.gov)
In the hyperadrenergic phenotype, the “adrenaline dump” is less like a random one-off and more like the body’s repeated upright pattern. When you stand, blood pressure tends to rise rather than fall: the Heart Rhythm Society consensus describes hyperadrenergic POTS as a systolic blood pressure increase of ≥10 mm Hg during 10 minutes upright, with standing plasma norepinephrine ≥600 pg/mL. That high upright norepinephrine is why the episode can feel as if your nervous system has slammed the gas pedal: racing heart, tremor, internal shaking, heat or flushing, wired anxiety, and a sense that your body is overreacting to something as ordinary as standing still. (pmc.ncbi.nlm.nih.gov)
This does not mean every surge is “just hyperPOTS,” and it does not mean you can subtype yourself by vibe. Clinicians usually need the full pattern: what happens to heart rate and blood pressure when you lie down, stand, or tilt; whether symptoms are orthostatic; what medications or stimulants are in the picture; and, in selected cases, supine and upright catecholamines. The same “amped” feeling can also come from panic attacks, arrhythmias, thyroid disease, low blood sugar, anemia, medication effects, mast-cell flares, or other conditions. (pmc.ncbi.nlm.nih.gov)
Subtype matters for treatment, and some drugs used in one phenotype are unhelpful or harmful in another — this is a clinician's call, not a self-diagnosis. The Heart Rhythm Society consensus notes that medications blocking norepinephrine reuptake can worsen POTS symptoms, while patients with prominent hyperadrenergic features may be considered for different clinician-directed options than patients whose main issue is venous pooling or low blood volume. (pmc.ncbi.nlm.nih.gov)
What actually helps
In the moment. Treat the surge like an orthostatic problem first. Get horizontal if you can; if you can’t, sit and raise your legs. That position uses gravity to send more blood back toward your heart and brain — it is physiology, not weakness. Cool your body next: move out of heat, loosen layers, put cool water on your wrists or face, or use a fan if you have one. Heat can dilate blood vessels and make PoTS symptoms worse, so cooling is not cosmetic; it reduces one of the body-level triggers keeping the surge alive. If your clinician has cleared salt and fluids for you, sip fluids with salt or electrolytes rather than trying to “push through” dry. If you have compression on hand, especially abdominal and leg compression, use it to reduce blood pooling. And while you wait for the wave to pass, make the exhale longer than the inhale — not because this is “just anxiety,” but because slow diaphragmatic breathing can help lower heart rate and shift the nervous system toward its calmer parasympathetic side. (potsuk.org)
In the pattern. Fluid and salt targets, compression garments, and any medication are individual and must be set by a clinician — salt loading is not safe for everyone, including people with high blood pressure or kidney disease. The part you can often shape day to day is the terrain your nervous system is standing on: protect sleep, because poor sleep can worsen autonomic instability; split meals into smaller, steadier ones, because large or high-carbohydrate meals can pull blood toward digestion and aggravate symptoms; and pace across the week, not just across the day. If a surge leaves you wired, shaky, foggy, or flattened afterward, don’t spend the next 24 hours “catching up” as if nothing happened. Build in recovery time on purpose. In PoTS, recovery is not laziness — it is part of lowering the next trigger load. (potsuk.org)
When to see a doctor
See a clinician promptly if these surges are new, changing, happening more often, or no longer follow your usual POTS pattern. A POTS adrenaline dump can feel like a body alarm — racing heart, shakiness, sweating, chest tightness, breathlessness, dizziness, near-fainting — and those symptoms can be part of POTS. But the same inside-the-body feeling can also come from an abnormal heart rhythm, an overactive thyroid, anemia, low blood sugar, medication effects, or another condition your clinician has to rule out with an exam and, often, basic heart and blood tests. (my.clevelandclinic.org)
Seek immediate care — call emergency services rather than waiting it out — if you have chest pain or pressure, fainting rather than near-fainting, shortness of breath at rest, unusual sweating with palpitations, a resting heart rate that stays unusually high for you, or symptoms that feel new and severe. Also treat one-sided weakness or numbness, trouble speaking, confusion, sudden vision changes, sudden loss of balance, or the worst sudden headache as emergency symptoms, even if they fade after a few minutes. (medlineplus.gov)
If you’re wondering is POTS dangerous, the honest answer is: POTS itself is usually not considered life-threatening, but fainting can injure you, and “this feels like my usual dump” is not a safe diagnosis when the pattern changes. Dramatic does not always mean dangerous — and familiar does not always mean harmless. Getting checked is how you separate a miserable autonomic surge from something that needs urgent treatment. (my.clevelandclinic.org)
How to bring this up with your doctor — and what to ask for
Bring a log, not a story. Not because your story does not matter — because your body is easier to assess when the pattern is visible. For each surge, write down when it happened, what position you were in, what you had just been doing, your heart rate before and during if you have it, whether your blood pressure changed, how long the episode lasted, and what the next day looked like. “I get weird episodes” can sound vague in a rushed visit. “My heart rate jumps after standing, I shake, it lasts this long, and I’m wiped out the next day” gives your clinician something concrete to test.
The most useful ask is an orthostatic vitals check: heart rate and blood pressure measured lying down and then after standing. POTS is usually evaluated through history, physical exam, orthostatic vital signs, and often an ECG; standing or tilt-table testing may be used to show whether symptoms and heart rate changes happen with upright posture. (pmc.ncbi.nlm.nih.gov)
Also ask what should be ruled out before the episodes are labeled “just anxiety.” In POTS workups, clinicians often look for conditions that can mimic or worsen orthostatic tachycardia, including anemia and thyroid problems; glucose issues can also cause fast heartbeat, shaking, sweating, dizziness, anxiety-like feelings, or confusion, so it is worth mentioning if episodes cluster around meals, fasting, alcohol, illness, or diabetes medications. (pmc.ncbi.nlm.nih.gov)
If the pattern is strongly postural — worse upright, better lying down, triggered by standing, heat, showering, meals, or exertion — say that plainly. You are not asking your doctor to accept your self-diagnosis. You are asking them to test the physiology: heart rhythm, blood pressure behavior, blood volume clues, and common medical look-alikes. If the first visit cannot go deep enough, ask whether referral to cardiology, neurology, or an autonomic clinic makes sense, especially if the episodes include fainting, chest pain, an irregular rhythm sensation, new neurological symptoms, or a sudden change from your usual pattern. (my.clevelandclinic.org)
What this looks like on a real week
The shape people describe matches the shape in the data. The surge arrives at rest — evening, sitting down, nothing dramatic happening. Heart pounding, hands shaking, heat in the face, a body that will not settle on command. By morning the storm is over and the obvious symptoms are gone, so the day gets planned as a normal day.
What our data says is that the body has not finished. On 88% of those next days, resting heart rate is still measurably above that person's own baseline — and on 64% of third days. The "why am I still wrecked, nothing is even happening" feeling has a physical correlate you can see in your own numbers, days after the episode everyone, including you, has already filed as over.
That is worth logging, not because it diagnoses anything, but because it changes what you can bring to an appointment. "I keep getting these terrifying surges" is hard for a clinician to work with. "Here is the episode, here is my resting heart rate for the three days after it, and here is what I could and couldn't do" is a timeline they can test against heart rhythm, blood pressure, medications, and the look-alikes worth ruling out.
How Welltory helps
Welltory does not diagnose POTS and does not measure adrenaline. POTS is diagnosed clinically, using your symptoms plus heart rate and blood pressure changes when you move from lying down to standing or during a tilt-table test — not by an app reading alone. (pmc.ncbi.nlm.nih.gov)
What Welltory can do is help you make the pattern visible. If your “adrenaline dump” tends to hit after standing, heat, a poor night’s sleep, a heavy meal, a stressful day, or too much activity, that pattern is easy to lose in memory and much easier to see in a log. You can track resting heart rate and HRV trends across days, repeat an orthostatic check the same way each time, and compare the day after a surge with your own baseline — not with someone else’s “normal.”
That matters because POTS symptoms can move through several systems at once: racing heart, shakiness, lightheadedness, fatigue, brain fog, chest discomfort, shortness of breath, sweating, nausea, and exercise intolerance can all cluster around standing or other triggers. (my.clevelandclinic.org) A clear record helps you describe the sequence: what happened first, how high your heart rate went, how long it stayed elevated, what helped, and whether the next day looked different.
Bring that log to your clinician. It will not replace an exam, ECG, blood pressure measurements, labs, or formal autonomic testing when those are needed. But it can turn “I keep getting these terrifying surges” into something more useful: “Here is when they happen, here is what my body does, and here is how long recovery takes.”
How we made it
Data. Welltory `persona_daily_panel`, snapshot of 2026-09-22: 4,145 users and 367,569 user-days (~88 days per user), filtered to `wearable_quality_ok = True`. Cohort flag `has_pots` is a self-report survey answer, not a clinical diagnosis: 359 users who self-report POTS against 3,786 comparison users.
Definitions. Every threshold is within-person, against that user's own mean and standard deviation, so nobody is measured against anyone else's "normal." Surge day: resting-HR z ≥ +1.0 with activity z ≤ 0 — a heart-rate rise not explained by moving more. Calm day: |resting-HR z| ≤ 0.5, same activity condition. Still elevated: resting-HR z ≥ +0.5 on the specified following day, counting only genuinely consecutive tracked days.
Controls we ran before publishing this.
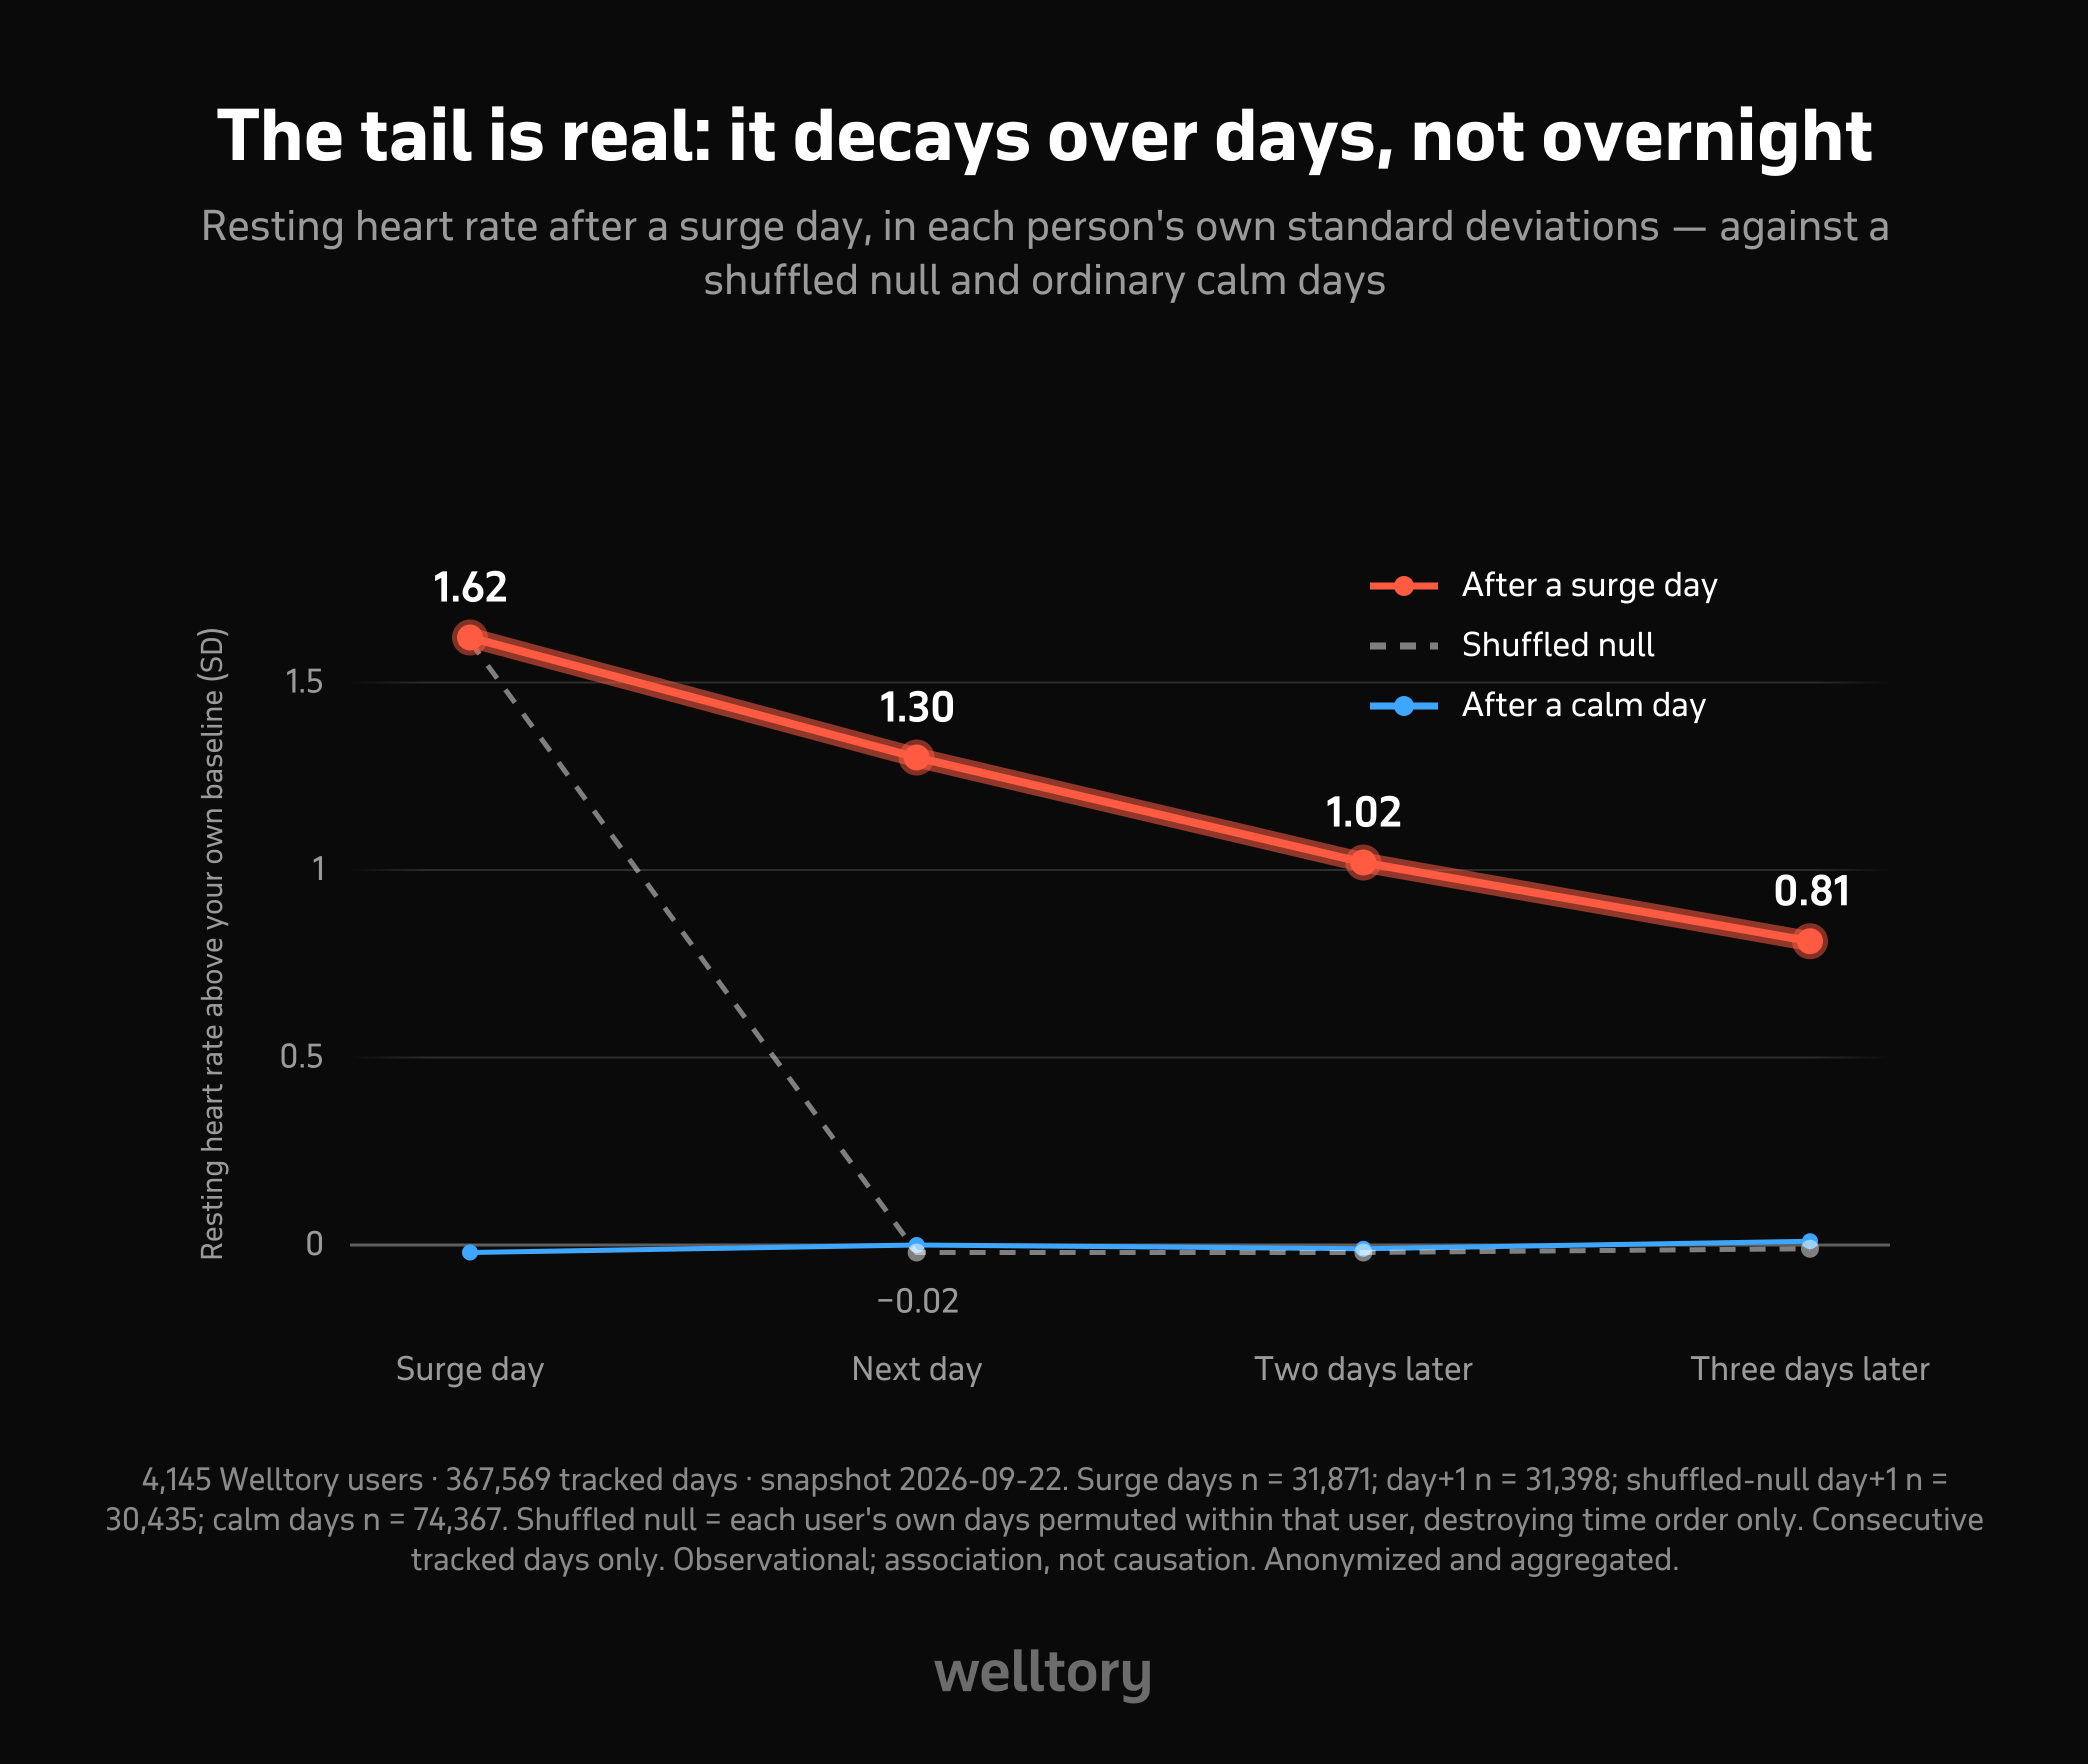
Shuffled null. Permuting each person's own days destroys the time structure; under that null only 29% of "next" days sit ≥0.5 SD high, against 88% in the real sequence. The persistence is temporal, not an artifact of the threshold.
Calm-day control. 16% after a calm day against 88% after a surge day — same people, same baseline, same activity filter.
Comorbidity stratification. The gap is flat in every stratum: +0.719 with no co-reported conditions, +0.714 with one, +0.731 with two, +0.715 with three or more. Not a "sicker people report more" effect.
Sensitivity. Restricting to users with ≥60 and ≥85 tracked days changes nothing (87.8% either way). Raising the surge threshold to 1.5 SD raises next-day persistence to 95%.
Limits. Observational and partly self-reported. Resting heart rate is a proxy for sympathetic load, not a measurement of adrenaline. People who track for three months may be healthier or more motivated than those who stop. And POTS is diagnosed by a stand or tilt-table test, not by an app. All figures are reported as anonymized, aggregated data; no individual user is identifiable.
The article itself was drafted with AI tools, then edited, fact-checked, and medically reviewed by the Welltory team.


Discounts for blog readers: up to 36% off
See what affects your energy, stress, sleep, and daily state with Welltory
This article is for educational purposes only and is not a substitute for medical advice, diagnosis, or treatment from a qualified clinician.
Was this helpful?
Ask AI for a summary of page


Written by Jane Smorodnikova

The founder and CEO of Welltory. A recognized tech leader with two Master's degrees and experience at MIT, she has scaled Welltory to over 17 million users.
Written by Tatsiana Yashyna

Deputy COO at Welltory. With a background in medicine and years of working with health data, she translates research and real physiological signals — sleep, stress, heart rate, and hormones — into clear, evidence-based explanations that help people understand what their bodies are telling them.
References
- Autonomic neurotransmission in cardiovascular regulation and pathophysiology. Frontiers in Neuroscience, 2025. https://doi.org/10.3389/fnins.2025.1739330
- Postural orthostatic tachycardia syndrome: mechanistic phenotyping and when dysautonomia misleads. Frontiers in Neurology, 2026. https://doi.org/10.3389/fneur.2026.1806502
- Peripheral Catecholamine Systems: An Evolutionary Perspective. PMC. https://pmc.ncbi.nlm.nih.gov/articles/PMC12824854/
- Bryant B, Knights K, et al. Epinephrine. StatPearls, NCBI Bookshelf. https://www.ncbi.nlm.nih.gov/books/NBK482160/
- Physiology, Catecholamines. StatPearls, NCBI Bookshelf. https://www.ncbi.nlm.nih.gov/books/NBK507716/
- Panic Disorder: When Fear Overwhelms. National Institute of Mental Health. https://www.nimh.nih.gov/health/publications/panic-disorder-when-fear-overwhelms
- Postural Orthostatic Tachycardia Syndrome (POTS). Dysautonomia International. https://www.dysautonomiainternational.org/page.php?ID=30
- Principles of Autonomic Medicine — orthostatic intolerance, norepinephrine and sympathetic noradrenergic activation. Dysautonomia International. https://www.dysautonomiainternational.org/pdf/PAM_4_WhatAreDys.pdf
- Symptoms of PoTS; Managing PoTS; Diet and Fluids. PoTS UK. https://www.potsuk.org/about-pots/symptoms/
- Postural Orthostatic Tachycardia Syndrome (POTS). Johns Hopkins Medicine. https://www.hopkinsmedicine.org/health/conditions-and-diseases/postural-orthostatic-tachycardia-syndrome-pots
- Postural Orthostatic Tachycardia Syndrome (POTS). Cleveland Clinic. https://my.clevelandclinic.org/health/diseases/16560-postural-orthostatic-tachycardia-syndrome-pots
- Heart Palpitations. Cleveland Clinic. https://my.clevelandclinic.org/health/diseases/17084-heart-palpitations
- Postural Orthostatic Tachycardia Syndrome: A Concise and Practical Guide to Management and Associated Conditions. PMC. https://pmc.ncbi.nlm.nih.gov/articles/PMC5267948/
- Postural Orthostatic Tachycardia Syndrome (POTS): State of the Science, Clinical Care and Research. NHLBI, NIH. https://www.nhlbi.nih.gov/events/2019/postural-orthostatic-tachycardia-syndrome-pots-state-science-clinical-care-and-research